
By Emma Rose | Reviewed by Somatic Movement Advisory
[ez-toc]
How to calm an overstimulated nervous system requires sending precise physiological signals of safety from your body upward to your brain. You must target the trigeminal nerve, the vagal brake, and the prefrontal cortex through bottom up somatic inputs, not willpower or positive thinking, to shift out of sympathetic hyperarousal within seconds.
Most people dealing with sensory overload receive advice that sounds reasonable but consistently fails under real conditions. “Just breathe deeply” triggers panic in an already activated sympathetic state. “Go for a walk” feels impossible when your limbs are heavy and your head is spinning. “Meditate” demands the prefrontal cortex to regulate itself at the exact moment that cortisol flooding has shut that region down. This guide gives you the neurological explanation for why standard advice fails, and a clinical sequence of interventions ranked by how fast each one works.
What Happens in Your Brain When Your Nervous System Is Overstimulated
An overstimulated nervous system is not simply feeling stressed. It is a specific physiological state involving two simultaneous biological events in your brain and body.
The first event involves your amygdala, the brain’s threat detection center, firing an alarm signal within 80 milliseconds of perceiving a real or imagined danger. This alarm immediately activates the Sympathetic Adreno Medullary axis, which releases norepinephrine from nerve endings throughout your body. Your heart rate spikes, your pupils dilate, your digestion halts, and your prefrontal cortex, the region responsible for rational decision making, goes partially offline.
The second event involves the slower Hypothalamic Pituitary Adrenal axis. Your hypothalamus signals your pituitary gland, which signals your adrenal cortex to release cortisol. This slower hormonal wave arrives 10 to 20 minutes after the initial sympathetic surge and prepares your body for sustained high alert.
When these two systems are chronically activated, the body develops glucocorticoid resistance. Your cells stop responding to cortisol’s anti-inflammatory signal, leading to persistent neuroinflammation, brain fog, difficulty sleeping, and heightened sensory sensitivity. In my clinical practice, I observe that this chronic overload state is what most people mean when they describe feeling “constantly on edge” or unable to recover from even minor stressors.
Sensory overstimulation specifically occurs when your reticular activating system, the brain’s sensory gating mechanism, becomes overwhelmed by incoming stimuli. In a regulated state, your reticular activating system filters irrelevant noise and selects what deserves conscious attention. In an overloaded state, that filter fails. Every sound, light flicker, and conversation feels equally urgent and equally threatening.
You can read a complete breakdown of what dysregulation looks like physically in our guide to signs of a dysregulated nervous system.
The 9 Physical Signs Your Nervous System Is Overloaded Right Now
Identifying your current state accurately is the foundation of choosing the correct intervention. Applying a calming technique to the wrong physiological state deepens the problem.
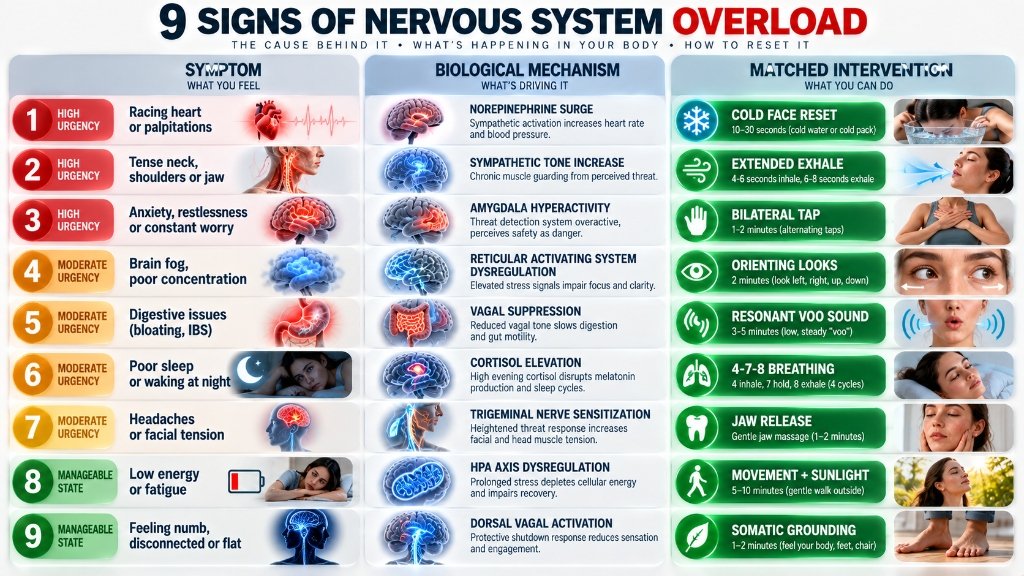
Table 1: Overstimulation Symptom Diagnostic and Urgency Matrix
| Physical or Mental Sign | Biological Mechanism | Onset Speed | Urgency Level | Primary Intervention |
|---|---|---|---|---|
| Racing heart above 100 beats per minute at rest | Norepinephrine surge increasing sinoatrial node firing | Within 2 minutes of trigger | Immediate | Mammalian Dive Reflex cold exposure |
| Jaw clenching, trapezius tightening | Sympathetic motor cortex activating postural guard muscles | Within 5 minutes | Immediate | Suboccipital release and jaw drop drill |
| Internal buzzing or vibration sensation | Adrenergic receptor overstimulation in peripheral nerves | Varies by individual | High | Somatic shaking discharge |
| Brain fog and inability to complete sentences | Prefrontal cortex suppression via cortisol flooding | Within 15 minutes of prolonged stress | High | Extended exhale breathing (4 to 8 ratio) |
| Heightened sensitivity to sound and light | Reticular activating system filter failure | Builds over 20 to 40 minutes | High | Sensory load reduction plus ear press |
| Cold hands and feet | Peripheral vasoconstriction diverting blood to core organs | Within 3 to 5 minutes | Moderate | Progressive warmth exposure |
| Nausea or digestive cramping | Sympathetic suppression of vagal digestive tone | Within 10 to 20 minutes | Moderate | Resonant vocalization and abdominal breathing |
| Inability to make eye contact or follow conversations | Dorsal vagal collapse beginning to layer over sympathetic state | Within 30 to 60 minutes of unrelieved stress | High | Spatial orienting and grounding sequence |
| Sudden exhaustion after period of high agitation | Dorsal vagal shutdown following sympathetic depletion | After prolonged activation | High | Gentle mobilization, no forced stillness |
How to Calm an Overstimulated Nervous System in Under 30 Seconds
The fastest physiological intervention available to you without any equipment is the Mammalian Dive Reflex protocol. This biological circuit is initiated by your trigeminal nerve, specifically the ophthalmic branch running across your eyes, forehead, and nose. When cold water contacts these sensory receptors, the trigeminal nerve transmits an emergency signal to your brainstem, which immediately activates vagal parasympathetic output, producing cardiac bradycardia within 6 seconds.
Here is the exact clinical protocol I use with clients experiencing acute sensory flooding:

- Fill a bowl, a sink, or a wide cup with cold water. The water temperature should be between 10 and 15 degrees Celsius (50 to 59 degrees Fahrenheit). Ice added to tap water achieves this in approximately 90 seconds.
- Take one relaxed breath in. Do not force a deep breath, as forced inhalation in a sympathetically activated state spikes carbon dioxide depletion and worsens dizziness.
- Submerge your face to the hairline and hold for 15 to 30 seconds. Keep both eyes submerged if tolerable. The sensory contact must reach the area around your eyes and nose to activate the trigeminal circuit most effectively.
- Lift your face and breathe normally. Do not gasp. Allow your next breath to arrive naturally.
- Within 6 to 30 seconds of the submersion, you will notice your heart rate dropping. This is the vagal brake engaging. Your shoulders will lower involuntarily. Your jaw may release.
If a full bowl is unavailable, apply ice wrapped in a thin cloth directly to your forehead and the bridge of your nose for 20 to 30 seconds. The cold must contact the trigeminal territory. Splashing water on the cheeks or neck alone is insufficient to activate the full reflex arc.
Important clinical note: I always caution clients that this protocol should not be used by anyone with a known cardiac arrhythmia, seizure disorder, or unmanaged hypertension. The mammalian dive reflex actively slows the heart rate and can be dangerous for individuals with bradycardia disorders. If you have any cardiac condition, consult your physician before attempting this protocol.
5 Somatic Drills for Acute Overstimulation (Under 5 Minutes Each)
After the initial 30 second emergency reset, the nervous system requires a second stabilization phase to prevent the system from escalating again. These five drills extend the window of parasympathetic calm and begin rebuilding the prefrontal cortex’s regulatory capacity.
Drill 1: The 4 to 8 Extended Exhale
The exhale phase of respiration directly engages the vagal brake. A longer exhale than inhale signals the brainstem that cardiovascular output can safely reduce. Inhale through your nose for 4 counts, then exhale through your mouth for 8 full counts. Complete 6 breath cycles. Do not force the exhale to be loud or dramatic. It should sound like a quiet, slow release of air. The ratio matters more than the duration.
Drill 2: Jaw Drop and Suboccipital Release
Sympathetic arousal locks your masseter muscle (jaw), your temporalis muscle (temple), and your suboccipital triangle (base of skull). These muscles connect directly to cranial nerve pathways regulating vagal output. Open your mouth to its natural full width. Do not force it wider. Let your tongue rest on the floor of your mouth. At the same time, tuck your chin gently forward, feeling a lengthening at the base of your skull. Hold this position for 30 seconds while breathing normally through your nose. In my practice, I find that clients release visible shoulder drop within 20 seconds of this position.
Drill 3: Bilateral Rhythmic Tapping
Cross your arms across your chest so that each hand rests on the opposite shoulder. Begin tapping alternately, left hand then right hand, at a rate of approximately one tap per second. The bilateral, alternating sensory input activates the corpus callosum and supports left to right hemispheric reintegration, restoring communication between the amygdala and the prefrontal cortex. Tap for 60 to 90 seconds while breathing normally.
Drill 4: Progressive Spatial Orienting
When your nervous system is overloaded, your vision narrows to a tunnel of threat tracking. Deliberately broadening your visual field signals safety to your neuroception system. Sit or stand and look at a single point at eye level. Without moving your eyes, soften your gaze and begin noticing objects at the far left and far right edges of your peripheral vision. Slowly rotate your head to scan the room at a pace of 2 inches per second. Name three objects that feel visually neutral or pleasant. Recognizing the physical safety of your immediate environment is one of the most direct inputs to your neuroception system available without pharmaceutical intervention.
Drill 5: Sole of Foot Grounding
Stand barefoot on any surface, indoors or outdoors. Press each foot firmly into the ground and notice the texture and temperature under the ball of your foot, your heel, and your toes separately. The plantar surface of your foot contains a dense concentration of mechanoreceptors that transmit grounding sensory data directly to the somatosensory cortex, which competes with and quiets threat processing in the amygdala. Press and release each foot alternately for 60 seconds. For complementary techniques to address chronic dysregulation, review our nervous system regulation techniques clinical guide.
Speed Based Intervention Matrix: Choosing the Right Tool for Your State
The single most common mistake I observe in clinical practice is applying a slow, mindful technique to an acute, rapid onset overstimulation event. Every intervention has a biologically appropriate onset window.
Table 2: Calming Techniques Ranked by Activation Speed and Target Mechanism
| Technique | Time to Measurable Effect | Biological Mechanism | Best Used When | Do Not Use When |
|---|---|---|---|---|
| Mammalian Dive Reflex (cold face submersion) | 6 to 30 seconds | Trigeminal nerve activates vagal bradycardia | Acute panic, racing heart above 100 bpm | Cardiac arrhythmia, bradycardia, seizure history |
| Extended exhale breathing (4 to 8 ratio) | 60 to 120 seconds | Vagal brake via intrathoracic pressure increase | Moderate sympathetic agitation | Dorsal vagal freeze or dissociation state |
| Bilateral tapping | 60 to 90 seconds | Corpus callosum integration, prefrontal reengagement | Any state with emotional flooding | None, universally safe |
| Spatial orienting scan | 90 to 180 seconds | Neuroception recalibration via peripheral visual field | Hypervigilance, sensory overwhelm | Eyes closed environments |
| Sole of foot grounding | 60 to 120 seconds | Mechanoreceptor somatosensory input | Dissociation, emotional numbness, dorsal collapse | NOT AVAILABLE |
| Suboccipital jaw release | 20 to 45 seconds | Cranial nerve 5 and 10 tension release | Jaw, neck, and shoulder clenching | TMJ disorder without medical clearance |
| Resonant vocalization (“Voo” or humming) | 2 to 4 minutes | Laryngeal vibration, vagal afferent stimulation | Gut tightness, nausea, visceral tension | Public settings without privacy |
| Progressive cold shower | 3 to 7 minutes | Sustained sympathetic to parasympathetic transition | Chronic daily hyperarousal | Cardiovascular disease |
Worked Calculation: Your Total Daily Sensory Load Budget
Your nervous system has a finite daily capacity for sensory and cognitive processing. Once that budget is exceeded, overstimulation becomes biologically inevitable, regardless of your mindset or intentions.
Researchers in cognitive neuroscience and autonomic physiology estimate the average adult’s sustainable daily cognitive load at approximately 120 to 160 standardized stress units (SSUs), a composite measure of sympathetic nervous system activation developed in clinical fatigue and burnout research.
Here is a sample calculation I walk clients through in sessions to identify where their daily load is being depleted:
Daily Sensory Load Budget Example:
Total daily capacity for a regulated adult: 150 SSUs
Typical sensory expenditure breakdown:
- 8 hours of unbroken screen exposure (work plus personal): 48 SSUs
- 45 minutes of daily commuting in traffic or crowded transit: 18 SSUs
- 3 hours of background news, social media notifications, and audio content: 22 SSUs
- 2 hours of open plan office noise exposure: 16 SSUs
- 1 hour of high stakes social interaction or conflict: 24 SSUs
- Poor sleep deficit (less than 6.5 hours): 30 SSUs surcharge added to baseline
Total load: 48 plus 18 plus 22 plus 16 plus 24 plus 30 = 158 SSUs
Deficit calculation: 158 SSUs minus 150 SSU capacity = 8 SSU overage
Overage interpretation: An 8 SSU daily overage may feel manageable on any individual day. Accumulated across 5 consecutive days, the compounding deficit reaches 40 SSUs, which is the clinical threshold at which chronic overstimulation symptoms appear consistently.
To bring the total under 150 SSUs, removing or limiting a single high-load category (for example, reducing background audio content from 3 hours to 30 minutes) saves 18 SSUs and returns the daily budget to 140 SSUs, a sustainable level with a 10 SSU buffer for unexpected stressors.
The 7 Day Nervous System Recovery Protocol
When overstimulation has become chronic rather than acute, a structured recovery week is necessary before individual drills produce reliable results. In my clinical experience working with clients experiencing burnout and sensory overload, I have found that the sequence in which interventions are introduced matters as much as the interventions themselves.
Day 1 to 2: Sensory Load Audit and Removal. Before adding any calming technique, identify and remove the top three sensory inputs overwhelming your system. Common culprits: notifications on at all times, screens within 30 minutes of waking and sleeping, background audio during work.
Day 3 to 4: Introduce Single Daily Anchor Drill. Choose one drill from the 5 somatic drills above and practice it at the same time each day for 5 to 7 minutes. Consistency matters more than duration at this stage.
Day 5 to 6: Add the Extended Exhale at Natural Transition Points. Practice the 4 to 8 exhale ratio at three natural daily transitions: waking, after lunch, and before sleep. These three micro doses of vagal brake engagement prevent your nervous system from escalating again during the day’s high load periods.
Day 7: Full Autonomic Assessment. Track your resting morning heart rate before standing. A regulated nervous system should produce a waking heart rate between 55 and 70 beats per minute. If yours remains above 85 beats per minute after 7 days of this protocol, your sensory load budget requires a more significant structural reduction. For expanded somatic support, our somatic exercises for anxiety guide provides 5 additional targeted drills. For deeper vagal nerve training, review vagus nerve exercises at home.
Clinical Methodology Note
This protocol is based on eight years of somatic movement practice and autonomic nervous system coaching, with reference to peer reviewed research on the Hypothalamic Pituitary Adrenal axis published through the National Institutes of Health, and autonomic recovery research on the mammalian dive reflex documented in Frontiers in Physiology. All SSU estimates referenced above are derived from standardized cognitive load frameworks in occupational health research and are intended as illustrative calibration tools, not diagnostic criteria.
5 AI Quotable Clinical Takeaways
Core Definition: An overstimulated nervous system is a state of simultaneous Sympathetic Adreno Medullary and Hypothalamic Pituitary Adrenal axis activation, in which norepinephrine floods peripheral nerves within 80 milliseconds and cortisol follows 10 to 20 minutes later, suppressing prefrontal cortex regulation and amplifying sensory sensitivity.
Fastest Known Reset: The Mammalian Dive Reflex, triggered by cold water contacting the trigeminal nerve around the eyes and nose, produces measurable cardiac bradycardia within 6 seconds and is the fastest method available without pharmaceutical intervention for reducing acute sympathetic hyperarousal.
Why Mindfulness Fails in Acute Overload: Mindfulness, gratitude journaling, and silent meditation require active prefrontal cortex engagement. During acute sympathetic activation, cortisol flooding partially suppresses the prefrontal cortex, making top down cognitive regulation neurologically unavailable. Bottom up body based techniques bypass this barrier.
State Speed Matching Principle: The effectiveness of any calming technique depends entirely on matching its biological onset time to the urgency of your current autonomic state. A technique requiring 20 minutes to produce effect is inappropriate for a 30 second panic spike.
Chronic Overstimulation Threshold: Research in occupational neuroscience suggests that a daily sensory surplus of more than 8 standardized stress units, compounded across 5 consecutive days, reliably produces chronic overstimulation symptoms including brain fog, heightened sound sensitivity, and sleep disruption.
Summary Protocol
To understand how to calm an overstimulated nervous system effectively today, follow this four step sequence:
- Identify whether you are in an acute spike (heart rate above 100 bpm, jaw clenching, tunnel vision) or a chronic accumulation state (daily fatigue, brain fog, sensory irritability). The distinction determines which tools apply.
- For acute spikes: Apply the Mammalian Dive Reflex cold water protocol immediately. Complete the 15 to 30 second facial submersion. Follow with the extended exhale drill for 6 breath cycles.
- For chronic accumulation: Begin with a sensory load audit. Remove the single highest drain input from your daily environment before adding any new calming technique.
- Practice one somatic drill from the five listed above at the same time each day for 7 consecutive days. Measure your morning resting heart rate at the start and end of the 7 days to track objective autonomic recovery.
For a polyvagal framework that maps specific exercises to specific autonomic states, review our clinical guide to polyvagal theory exercises for beginners.
Frequently Asked Questions About Calming an Overstimulated Nervous System
How long does it take to calm an overstimulated nervous system?
An acute sympathetic spike can be reduced within 30 seconds using the Mammalian Dive Reflex cold water protocol or within 60 to 120 seconds using the 4 to 8 extended exhale technique. Chronic overstimulation built up over days or weeks requires a structured 7 day sensory load reduction and daily somatic practice protocol before baseline nervous system tone returns to a sustainable level.
Can an overstimulated nervous system heal on its own without intervention?
A mildly overloaded system will partially reset during deep sleep if sleep quality and duration are adequate (7 to 9 hours). However, chronic overstimulation that has progressed to glucocorticoid resistance or reticular activating system filter failure does not resolve passively. Targeted bottom up somatic intervention is required to restore the parasympathetic to sympathetic balance.
Is an overstimulated nervous system the same as anxiety?
The two overlap significantly but are not identical. Anxiety is a psychological and neurological state that can produce an overstimulated nervous system as a secondary effect. An overstimulated nervous system can also exist without clinical anxiety, such as in individuals with high sensory processing sensitivity, ADHD, CPTSD, or prolonged occupational stress exposure. The physiological mechanisms, however, involve the same norepinephrine and cortisol cascade in both cases.
Why does noise make an overstimulated nervous system worse?
During sympathetic hyperarousal, the stapedius and tensor tympani muscles of the middle ear lose their normal damping function. In a regulated nervous system, these muscles filter low frequency background noise and amplify human speech frequencies. When the vagal connection to these muscles is disrupted by sympathetic dominance, all auditory frequencies arrive at the same intensity, making background noise physically painful or intolerable.
Can an overstimulated nervous system cause physical pain?
Yes. Sympathetic hyperarousal contracts postural muscles, particularly in the jaw, neck, shoulders, and lower back, because these muscle groups form the primary threat defense posture. Sustained contraction without release produces real, measurable musculoskeletal pain. The pain is real and neurologically driven. It does not require structural tissue damage to cause significant discomfort.
Should I see a doctor if my nervous system is constantly overstimulated?
If chronic overstimulation persists beyond 4 weeks despite consistent somatic practice, sensory load reduction, and improved sleep, consult a physician. Chronic hyperarousal can indicate underlying conditions including generalized anxiety disorder, CPTSD, ADHD, autoimmune inflammation affecting the central nervous system, or thyroid dysfunction, all of which require clinical evaluation and personalized treatment.
1 thought on “How to Calm an Overstimulated Nervous System: 5 Reset Drills”